Interoception and the Sense of Self: A Thematic Analysis

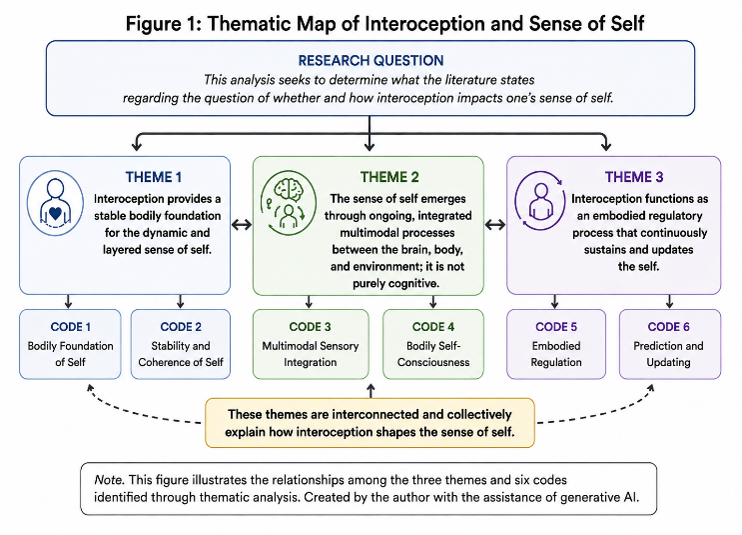
Research Question: This analysis seeks to determine what the literature states regarding the question of whether and how interoception impacts one’s sense of self.
Introduction: According to a recent population-based study of U.S. adults, 3.8% met diagnostic criteria for ICD-11 complex posttraumatic stress disorder (CPTSD), compared with 3.4% who met criteria for PTSD (Cloitre et al., 2019). PTSD is characterized by symptom clusters of affect dysregulation, negative affect and cognition, re-experiencing of the event in the form of flashbacks, nightmares, sensations, or emotions, and avoidance of reminders of the event, while CPTSD includes those symptoms as well as difficulties in interpersonal relationships and sense of self. The consequences of these often debilitating disorders are far reaching, impacting nearly every domain of an individual’s life, including their ability to be functioning members of society and experience a sense of well-being (Cloitre et al., 2019). Furthermore, the impact of these disorders comes with a significant societal and economic cost (Zaccari et al., 2023).
The gold standard treatment often recommended are forms of psychotherapy referred to as talk therapy, such as Cognitive Processing Therapy or Cognitive Behavioral Therapy. Increasingly more research is suggesting that these forms of therapy, often referred to as a top-down approach to treatment, eluding to its focus on cognitive and behavioral aspects, is ineffective in treating mental health issues where there is unaddressed underlying affective and bodily dysregulation, as is often the case with disorders stemming from trauma (Hauke & Critchley, 2026; Van Der Kolk et al., 2014; Zaccari et al., 2023). In a randomized control trial (RCT) conducted by (Zaccari et al., 2023), researches sought to determine the efficacy of Trauma Center Trauma Sensitive Yoga (TCTSY) compared with Cognitive Processing Therapy (CPT), considered the Veteran’s Affair’s gold standard in the treatment of PTSD, on women veterans who had experienced military sexual assault. TCTSY, a bottom-up, or body based practice was developed for women with CPTSD and are survivors of childhood sexual abuse. Unlike top-down, cognitive approaches to treatment, TCTSY “focuses on reducing stress reactions of the body by cultivating interoception” (Zaccari et al., 2023). Researchers found that CPT, although effective, had a high attrition rate, lacked acceptability by treatment participants, and had an incomplete treatment effect, leaving over half of the people who completed treatment with a continued PTSD diagnosis. Consequently, many people who are living with the impact of trauma, both CPTSD and PTSD, report being unable or unwilling to participate in talk therapy due to the emotional flooding and physiological overwhelm that ensues when recalling and discussing aspects of the trauma in therapy. The RCT results indicated that not only was TCTSY as clinically effective in reducing or eliminating symptoms of PTSD, but it also had a higher retention and completion rate (42.6% higher), suggesting that this body-based treatment, with its focus on interoception, may lead to more people receiving and completing treatment. Furthermore, it was found to be more cost-effective due to lower cost of participating in a group treatment (Zaccari et al., 2023).
Theoretical Underpinning. Herman (1992) asserts that those who are subjected to a relationship that inflicts coercive control profoundly alters the survivor’s experience of who they are, adding that "all the structures of the self—the image of the body, the internalized images of others, and the values and ideals that lend a sense of coherence and purpose—are invaded and systematically broken down” (p. 385). She continues to argue that survivors of chronic, or complex trauma are left with feelings of hypervigilance, rage, anxiety, agitation and experiences of depression, suicidal ideation, and dissociation “without any recognizable baseline state of calm or comfort” (p. 380) and that complex CPTSD has pervasive and corrosive impacts on the person’s sense of self, affect regulation, and interpersonal relationships above and beyond the impact of specific event related PTSD. Body-based treatments for trauma, such as TCTSY, which is grounded in trauma theory, attachment theory, and neuroscience aim to treat trauma at the root in the underlying physiological dysregulation, through their focus on building capacity for body awareness and tolerance of physical and emotional experience in the body (Zaccari et al., 2023).
Aim 1: To examine how the literature conceptualizes the relationship between interoception and the sense of self.
Aim 2: To examine the role of interoception in body ownership as a specific aspect of an embodied selfhood.
Data Collection. Data for the analysis was collected by searching Smith College’s online library for peer-reviewed literature using combinations of the keywords “interoception”, “interoceptive”, “body awareness”, “sense of self”, “self-concept”, and “self-coherence”. Articles that discussed the relationship between interoceptive processes and sense of self or related concepts or phrases were included and articles that only discussed interoception and its relationship to emotion regulation or physiological regulation with no reference to the impact on sense of self were excluded. Data were stored in encrypted cloud storage which requires two passwords to access. Additionally, handwritten notes were stored in a locked filing cabinet in a room with a locked door. No human subjects or identifiable information was used in this study and the data consisted entirely of published literature, so there was no additional need for measures of confidentiality.
Due to my position as a Somatic Experiencing Practitioner, trauma sensitive yoga facilitator, and somatic oriented psychotherapist, I have an existing familiarity with body-based practices and concepts related to body-awareness and nervous system regulation. Additionally, I entered into this project already having a strong interest in the relationship between somatic experiences and psychological functioning that may have predisposed me to viewing interoception and other bodily processes as meaningful and influential. This may have influenced the articles that I chose to include in the analysis and what stood out to me as significant in the data. My existing experience and knowledge of the field provides me with the ability to notice details that other researchers may not but also makes me more likely to privilege embodied explanations to the findings around psychological functioning. To address this, I returned repeatedly to the actual language used in the articles and kept my codes in alignment with the intended meaning. Additionally, I intentionally scanned the articles for data that complicated or did not fit my initial assumptions and included those findings in the analysis.
Method
Data interpretation: An inductive thematic analysis of the selected literature was conducted to identify patterns in how interoception is described in relation to the sense of self.
Thematic analysis was utilized due to its ability to systematically identify, organize, and provide insight into patterns of shared meaning across a data set, with the goal of elucidating how these patterns address the research question. Inductive analysis was predominantly appropriate for this study because I let the codes and themes come directly from the data (Braun & Clarke, 2012). Following the Braun & Clarke (2012) methodology for thematic analysis, the process began with an initial read through of each of the articles to begin to familiarize myself with the data while highlighting words and phrases that were broadly associated with interoception and sense of self. I then repeated this process a second time while also looking for patterns and underlying meaning across articles. From these two passes I began generating initial codes which were based off my interpretation of what the data was describing. I then began to collate the data extracts from which the code originated into a spreadsheet. These codes and associated data were then grouped into categories, which later became the themes and the analysis flowed from the codes, themes, and excerpts. The purpose of this analysis was to examine whether and how interoception relates to the concept of sense of self. The analysis of the included literature resulted in three distinct, yet interconnected themes that offer an understanding of the stated research question.
Results
Theme 1: Interoception provides a stable bodily foundation for the dynamic and layered sense of self. Across all articles, there was a clear and consistent consensus that interoception, defined by Quigley et al. (2021) as “the overall process of how the nervous system (central and autonomic) senses, interprets, and integrates signals originating from within the body, providing a moment by moment mapping of the body’s internal landscape across conscious and unconscious levels” (p. 29), is foundational to one’s sense of self, or self-concept. The concept of a self, although abstract, has a quality of stability to it, while also remaining dynamic and malleable. (Hauke & Critchley, 2026) describes “the self as a dynamic, physically anchored process whose core is interoception – the continuous processing of internal bodily signals as the basis of subjective presence and affective self-perception” (p. 2). The self and the body, it would seem, are not separate entities, but interwoven processes that together form an embodied selfhood. Interoception influences many aspects of the self, contributing to its stability over time and helps to solidify and integrate the various layers of self, which consist of reflective layers, bodily layers, and unconscious, pre-reflective layers. This stability and coherence act as a protective factor against external influences that might serve as a negative influence that steers one away from their authentic self. Tsakiris (2017) speaks to the fundamental role interoception plays in “the unity of the self because interoception is required for the experience of a unified, non-hollow self, and to its stability because interoception can counteract the ever-changing influence of exteroceptive signals” (p. 600). Individuals who are more tuned in with the language of the body, which is broadcast through internal signals such as sensation, have a deeper sense of knowing who they are and who they are not when faced with external information or influence. The body acts as a frame of reference against which to determine what feels like “me” and what feels like “not me” and this distinction is felt in the body. However, if we were to claim that the mechanism underlying the sense of self is entirely mediated by interoception we would not be providing a complete and accurate picture. The pattern across the reviewed literature is that although interoception is foundational to sense of self, it is not interoception alone that the sense of self is built upon, but rather an integrated process between the brain, the body, and the environment.
Theme 2: The sense of self emerges through ongoing, integrated multimodal processes between the brain, body, and environment; it is not purely cognitive. One’s sense of self is also not solely a cognitive, or reflective function as it is commonly understood and described in the literature and colloquially. Alternatively, our sense of selfhood is also not singularly mediated by bodily processes. As one article so eloquently proposes “whenever we think of ourselves, we think with our body and not just with our mind” (Monti et al., 2022, p. 2473) capturing the multimodal input of the self. Although it is agreed that interoception is foundational to the sense of self, it does not do the work of organizing the self on its own. Findings suggest that it is much more complex, involving multimodal processes, such as sensory information from inside the body, the external environment as well as cognitive processes. “Such multisensory coupling is thought to generate both the sense that the physical body and its parts belong to “me” (body ownership) and the sense that “I” am the agent causing actions and their effects in the external world” (Hauke & Critchley, 2026, p. 3) and that “the experience of body ownership, a key aspect of selfhood, is modulated by predictive multisensory integration of precision-weighted interoceptive and exteroceptive signals” (Seth, 2013, p. 571). These data suggest that what it means to have a sense of self is not only supported by these multiple bodily processes, but that the sense of having a body is part of that sense of self. We simply cannot be separated by our parts. Body, mind, and environment exist in relationship with each other.
While interoception is the process of picking up cues from within the body, such as visceral sensation, air hunger, temperature, heartbeat, muscle tension, respiration patterns, and physiological arousal, exteroception is the processes of receiving sensory information about the body coming from the outside of the body (Tsakiris, 2017), such as through the five basic senses. These multi-sensory processes are integrative and supportive of a cohesive and stable self-concept over time and when only one pathway is fully functioning, deficits in self and regulation are experienced. One way this was shown was through a study that found a “negative correlation between levels of interoceptive awareness (IA) and malleability of self-awareness, as a result of multi-sensory exteroceptive input” (Quigley et al., 2021, p. 35). In other words, the lower one’s IA, the stronger the impact on a sense of body ownership, “suggesting [that in] the absence of accurate interoceptive representations, one's model of self is dominated by exteroceptive input” (Quigley et al., 2021, p. 35). This means that one’s sense of self becomes more easily influenced by the external environment and the individual is less likely to self-reference or trust an internally driven sense of self. Conversely, studies have shown that those with higher interoceptive accuracy are less negatively influenced by competing information from the external environment (Tsakiris, 2017). When there is enough of an ability to sense and accurately identify internal signals, you are less likely to be influenced or swayed by external signals.
This bi-directional process is continually updating the representation of self as new information is received from inside the body and from the external environment. This dynamic, as opposed to fixed, process is necessary because context is continually changing. In other words, our sense of selves, how we view ourselves and the world changes through experience. This constant flow of information through our physiology interacts with and influences the meanings we make from these experiences. For example, imagine someone walks into a classroom to give a presentation in front of their classmates. They notice their heart rate start to increase and their palms start to sweat (interoceptive signals), they see the smiling faces and relaxed postures of their classmates (external cues), and simultaneously they have a recognition that they have done this before and enjoyed it, an interpretation is made of their own internal body signals and their classmates body language (cognitive processes). All of this information, taken in from multiple sources, contributes to the person’s experience of themselves in that moment, as “I’m nervous, but I’ve got this. I know I am capable and even if I stumble I know I can handle it.” It is not only the thought that informs who they are and it is not only the racing heart or the smiles on their classmates faces. It is through the bi-focal lens of both mental processes and sensory input from internal signals and external cues that this meaning is born and contributes to a sense of self.
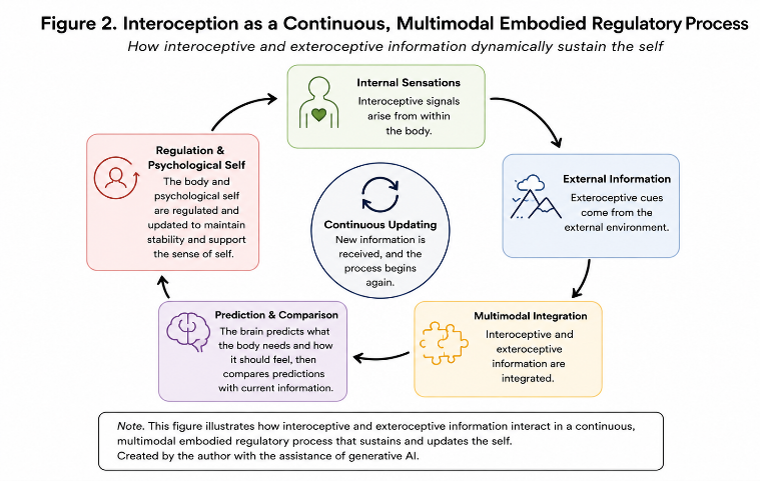
Theme 3: Interoception functions as an embodied regulatory process that continuously sustains and updates the self. The process of interoception is dynamic and is continuously working to sustain regulation of physiology and the psychological self, updating it when new information is received by the body and environment. Quigley et al. (2021) states that “interoceptive and exteroceptive sense data are continually predicted and used by the [central nervous system] to maintain allostasis and, in the process, make meaning about the relationship between one’s body, its predicted needs, and the external world (p. 30). What this is proposing is that the brain is a prediction machine, meaning it is continually making predictions about what it thinks the body needs, what it should feel like, and what state it should be in. It then compares those predictions with the present moment information that interoception provides about what is actually happening. When the information does not match what was predicted, it generates a prediction error (Tsakiris, 2017). Seth (2013) states that “prediction errors can be minimized either by updating generative models … or by performing actions to bring about sensory states in line with predictions” (p. 566), meaning the brain can then either update its understanding, or it can begin to initiate processes or behaviors with the goal of changing the body’s internal state so that it more closely matches what was expected or is needed to maintain homeostasis. But it is not only regulating and updating the physiology. "In humans, self-related predictive coding simultaneously engages multiple levels of self-representation, including physiological homeostasis, physical bodily integrity, morphology and position, and - more speculatively - the metacognitive and narrative 'I'” (Seth, 2013, p. 570). Through this process it is continually working to sustain and update the self, keeping the internal milieu in regulation, adapting based on a changing environment, both internally and externally. Each mode playing a distinct role in the process; interoception does the job of stabilizing the self, while exteroception aids in its malleability. When external information conflicts with reliable internal bodily information, interoception can resist it. When external information matches reliable internal bodily information, interoception can strengthen it. Both are needed in order to maintain cohesiveness in an ever-changing environment.
The stability and coherence of the self-representation that is achieved through interoceptive regulatory processes is found to impact one’s mental wellness in important ways. People who are more attuned to their internal bodily signals “describe themselves as more self-disciplined, more resilient, and more self-centred, as they cope better with social exclusion, tend to prioritise their own needs over those of the others, and are more prone to act selfishly” (Quigley et al., 2021, p. 2472), “impact on how one perceives one's own moral temper and character” (Monti et al., 2022, p. 2471), and “suggests that interoception may operate as a meaningful component of therapeutic change, acting as a transdiagnostic mechanism” (Aquino et al., 2026., p. 21).
Interoceptive signals can be thought of as arising on a continuum. For example, there is signaling that never rises to the level of conscious awareness, such as signals from the gut, the immune system, and endocrine system that one will never notice. Then there are the signals that can be detected consciously, such as heartbeat, respiration, muscle tension, temperature, and hunger. But it is not just the conscious signals that are shaping one’s sense of self, the unconscious signals are also influencing the self behind the scenes without you even knowing it. Quigley states that “interoceptive signals are typically in the background of phenomenal awareness (i.e., one does not focus attention on activity in one’s gut during all waking hours), interoceptive signals can sometimes be more or less foregrounded in attentional awareness” (2021, p. 35). This is important to note because although there are findings suggesting that interoception plays an important role “between physiological regulation and subjective meaning-making” (Aquino et al., 2026., p. 22), not all levels of interoceptive processes show the same impact. Aquino et al, (2026) points out an important distinction that these patterns were found to be mostly in studies that were using self-report measures of interoceptive sensibility, and that studies that instead used physiological assessments that measured interoceptive accuracy resulted in changes that were less consistent. Not all interoceptive capacities are the same. But this tendency to group them all together, is “a distinction that reflects a broader tendency in the reviewed literature to operationalize interoception through a top-down, reflective lens, emphasizing conscious monitoring, appraisal and cognitive interpretation of bodily sensations rather than pre-reflective bodily regulation” (Aquino et al., 2026, p. 22).
Discussion: When considered as a whole, these themes make a strong case for the salience of interoceptive processes in the development, stability, and coherence of one’s sense of self. Additionally, they illuminate how this is accomplished via multimodal sensory and mental processes, including reflective and pre-reflective levels of experience and input. An important finding was that it is not interoception alone that contributes to the self and that these concepts themselves are more complex and layered than is often conceptualized in both the literature and among lay persons. The distinction that there are multiple hierarchical levels to both the self and the interoceptive processes it is founded upon is something that needs to be more clearly stated in the discourse. This may lead to more robust and nuanced treatment modalities that serve to increase the usefulness of interoception on one’s sense of self and general wellbeing. Furthermore, with the understanding that exteroception is also a factor that contributes to the malleability of one’s sense of self, there is further opportunity to incorporate exteroception into treatment modalities, perhaps by increasing external cues of safety and reducing external cues of threat.
Predictive processing offers us a possible mechanism for understanding how interoception contributes to both the stability and adaptability of the self. Rather than conceptualizing the self as being fixed, predictive processing helps us to understand how the brain continuously compares its predictions about the body and its needs with incoming interoceptive and exteroceptive information. This allows an embodied and dynamic self to be both maintained and updated as conditions change in the internal and external environments.
These contemporary understandings are also reflected in earlier psychodynamic theories of the development of the self. Long before the emergence of modern interoception research made possible by neuroscience, Winnicott (1960) also postulated that the True Self emerged through bodily experience, describing it as arising from “the aliveness of the body tissues and the working of body-functions, including the heart’s action and breathing” (p. 148). Although Winnicott was not describing interoception as it is currently understood, he also understood that selfhood had its origins in embodied internal experience.
These multi-sensory and integrative regulatory processes work to safeguard the integrity of the self. The main agenda for any organism is ensuring its own survival-including the survival of the self. So interoception is imperative for not only the foundation of the sense of self, but more importantly, its very survival
Limitations: Although this analysis identified clear and consistent themes across articles, there were several limitations that are important to consider. The analysis was limited to a small sample of six articles, which likely only represents a small section of the relevant literature. The entire analysis was conducted by one author who conducted all the data collection, coding, and analysis, providing no inter-rater reliability. Additionally, my positionality as a Somatic Experiencing Practitioner and trauma sensitive yoga teacher which affords me prior knowledge and experience of somatic approaches and interoception may have led to researcher bias around what was included and what was emphasized in the findings.
Conclusion: This analysis began in the pursuit of determining whether and how interoception impacts sense of self and finished able to strongly assert that it is foundational to sense of self but it is not doing this on its own. There is an entire scaffolding of integrated processes occurring to cultivate and support the self, most notably exteroception and reflective processes. These findings support the notion that it is rarely one variable that explains complex abstract constructs such as our sense of self. It is a bottom-up, top-down, inside and outside, fully embodied regulatory process that lends itself to the complexity of what it means to be an embodied human self. Further research examining how disruptions in these processes affect the experience of self may be particularly valuable for understanding clinical conditions characterized by disturbances in embodiment and self-experience, such as PTSD and CPTSD. Furthermore, this study, along with others discussed in the literature review offer growing support to advocate for changes to policy and practice to begin including body-based practices that influence interoception as a means of reducing not only the physiological symptoms of trauma, but also the corrosive impacts of trauma on one’s sense of self in a manner that is more accessible, tolerable, and cost-effective.
References
Aquino, I., Dufey, M., Manríquez-Reyes, K., Castillo, F., Teixeira, S., Arellano, J., Jérez-Bravo, J., & Bacigalupo, F. (2026). A systematic review of interoception and therapeutic outcome research: Implications for psychotherapeutic practice. Psychology and Psychotherapy: Theory, Research and Practice, n/a(n/a). https://doi.org/10.1111/papt.70088
Braun, V., & Clarke, V. (2012). Thematic analysis. In APA handbook of research methods in psychology, Vol 2: Research designs: Quantitative, qualitative, neuropsychological, and biological (pp. 57–71). American Psychological Association. https://doi.org/10.1037/13620-004
Cloitre, M., Hyland, P., Bisson, J. I., Brewin, C. R., Roberts, N. P., Karatzias, T., & Shevlin, M. (2019). ICD-11 posttraumatic stress disorder and complex posttraumatic stress disorder in the United States: A population-based study. Journal of Traumatic Stress, 32(6), 833–842. https://doi.org/10.1002/jts.22454
Hauke, G., & Critchley, H. D. (2026). The heart of the self: An interoceptive perspective on the psychotherapeutic process. Consciousness and Cognition, 141, 104032. https://doi.org/10.1016/j.concog.2026.104032
Herman, J. L. (1992). Complex PTSD: A Syndrome in Survivors of Prolonged and Repeated Trauma. Journal of Traumatic Stress, 5(3), 377–391. (24853397). https://doi.org/10.1002/jts.2490050305
Monti, A., Porciello, G., Panasiti, M. S., & Aglioti, S. M. (2022). The inside of me: Interoceptive constraints on the concept of self in neuroscience and clinical psychology. Psychological Research, 86(8), 2468–2477. (160294411). https://doi.org/10.1007/s00426-021-01477-7
Quigley, K. S., Kanoski, S., Grill, W. M., Barrett, L. F., & Tsakiris, M. (2021). Functions of Interoception: From Energy Regulation to Experience of the Self. Trends in Neurosciences, 44(1), 29–38. https://doi.org/10.1016/j.tins.2020.09.008
Seth, A. K. (2013). Interoceptive inference, emotion, and the embodied self. 17(11).
Tsakiris, M. (2017). The multisensory basis of the self: From body to identity to others. Quarterly Journal of Experimental Psychology (2006), 70(4), 597–609. https://doi.org/10.1080/17470218.2016.1181768
Van Der Kolk, B. A., Stone, L., West, J., Rhodes, A., Emerson, D., Suvak, M., & Spinazzola, J. (2014). Yoga as an Adjunctive Treatment for Posttraumatic Stress Disorder: A Randomized Controlled Trial. The Journal of Clinical Psychiatry, 75(06), e559–e565. https://doi.org/10.4088/JCP.13m08561
Zaccari, B., Higgins, M., Haywood, T. N., Patel, M., Emerson, D., Hubbard, K., Loftis, J. M., & Kelly, U. A. (2023). Yoga vs Cognitive Processing Therapy for Military Sexual Trauma–Related Posttraumatic Stress Disorder: A Randomized Clinical Trial. JAMA Network Open, 6(12), e2344862. https://doi.org/10.1001/jamanetworkopen.2023.44862

You Can’t Manage Your Way to Regulation (Why Management Strategies Aren’t the Same as Regulation — and Sometimes Get in the Way)
You know that feeling when you’ve nailed your “regulation technique” — slowing down the breath, tapping, grounding — and in seconds you’re back to baseline? Gold star, right?
Except… maybe not.
Lately I’ve been noticing this cultural obsession with “nervous system regulation” — as if that’s the Holy Grail of healing.
We treat it like emotional Windex: just wipe down the messy stuff until it’s shiny again.
Or like emotional CrossFit — training ourselves to bounce back faster, look calm, and stay “in control” so we can keep on keeping on.
Back to our fast-paced, disconnected, yet “productive” lives, doing all the things.
We’ve turned “nervous system regulation” into a modern self-help sport.
Everyone’s breathing, plunging, and buzzing their vagus nerve like it’s the Olympics.
But here’s the thing: most of what’s being sold as “regulation” isn’t regulation at all.
It’s management.
It’s a quick fix — a nervous-system version of scrolling TikTok or reorganizing your spice drawer when life feels too big.
Management is a skill, a strategy — something we do to get through the moment, to contain, calm, redirect, soothe, or override discomfort.
And sometimes that’s exactly what’s needed.
It can help build confidence in our capacity to handle distress, and give our nervous system a glimpse of something other than chaos.
But management isn’t regulation — and it’s often used as a bypass, not a bridge.*
It might soothe things temporarily, but it’s not integrative or sustainable.
It certainly doesn’t renegotiate trauma or restructure your sense of self.
And it might just be masking underlying dysregulation.
When we rush to “calm down,” we often interrupt the body’s natural healing or emotional-completion process.
We skip the part where we actually feel what’s happening — the vulnerability, the contact, the messy middle where transformation and integration occur.
It’s like hitting the mute button on your body just when it starts to say something important.
If we were in relationship with someone who said “shhh” every time we had a big feeling, we’d call that dismissal or avoidance, not attunement.
But when we do it to ourselves, we call it “self-care.”
In shock trauma or PTSD, this can also interrupt the full expression of self-protective responses — fight, flight, protest, orient, or boundary-setting — and the energy mobilized to enact them.
Over time, this keeps us from standing up for ourselves, saying no, or living authentically with ease.
All that untapped energy doesn’t disappear — it gets trapped.
Pent up in the superhuman effort to hold back our own life force.
We end up stuck in a perpetual loop of mobilization and collapse — never fully returning to regulation.
And here’s the kicker: the idea of “reaching regulation” has become the new fountain of youth.
It’s an easy sell — who doesn’t want peace, balance, and ease?
But the snake oil isn’t regulation itself — it’s the promise that a few quick techniques can get you there.
These tools are being marketed as shortcuts to healing, as if you can breathe, buzz, or plunge your way into wholeness.
If it sounds too good to be true, it probably is.
(And honestly, if it were true, they’d be selling it at Target by now.)
There is no quick fix for trauma.
Quick and chronic is what caused it —
so slow and steady is what heals it.
And for people with complex trauma, this false promise can sting even more.
When “regulation” doesn’t work the way it’s advertised, it’s easy to assume you’re the problem.
You start believing you must be doing it wrong — or that your system is broken, too damaged, too much.
When really, it’s just doing what it’s had to do to survive — and the skills you’re using were never designed to do what was promised.
It’s not your failure; it’s faulty marketing.
Not all trauma is the same, and not all trauma is treated the same.
There is no one-size-fits-all.
Don’t get me wrong — management has its place and it’s valuable.
It’s essential when you’re driving, parenting, in a meeting, or just don’t have the bandwidth to go deeper.
It’s also fantastic for reducing stress and lowering the temperature, so to speak.
But if management (marketed as regulation) is the only muscle we work, we never build the capacity to relate — to stay present long enough for true regulation to emerge.
Here’s the deeper truth: regulation isn’t something you do.
It’s an emergent biological process.
Your body finds its own rhythm and balance when it finally feels safe enough, seen enough, and not under pressure to fix itself.
You can’t force it — you can only create the conditions for it.
We’ve confused managing our feelings with relating to them.
We calm down before we ever get curious.
We abandon the parts of ourselves screaming for recognition and repair.
We “ground” before we ever touch the ground of what’s real.
So these days, I’m less interested in how quickly someone can “regulate,” and more curious about how gently they can stay.
Management helps us survive.
Relating helps us heal.
And regulation? That’s what finally happens when the body feels safe enough to stop performing, complete what it started, and start trusting again.

You Cannot Heal in the Same State You Survived In
The Cycle of Trauma Dynamics
Most people don’t realize that the pressure they feel to “heal fast” is part of the same pressure and trauma dynamics that created their wounds in the first place. Urgency can feel like progress, like momentum — and it can also feel like threat. In reality, it is trauma repeating itself, creating unsafe internal conditions, and it is reinforced and perpetuated by unsafe external systems that are made of the same trauma dynamics. The social body itself is currently in a state of survival and we are all steeped in it.
The nervous system that learned to survive by rushing, pushing, pressuring, disconnecting, and overriding pain will try to bring that same strategy into the therapy space. And if we’re not careful, therapists and even entire systems can collude with it. We’re promised quick fixes, instant gratification, and “new “ therapies that will finally make everything better. It’s compelling — and it’s also misleading.
Because here’s the truth: urgency doesn’t heal trauma. It reenacts it. And the systems that benefit from your pain are counting on you to keep it up.
The Longing to Feel Alive Again
For many people seeking therapy or wellness practices, urgency shows up not just as anxiety, but as longing. After living with numbness, shutdown, or disconnection, people desperately want to feel alive again. To feel whole. And who could blame them? It is after all, our birthright. We were meant to be connected. Our physiological architecture is the manifestation of this promise waiting to be kept.
This longing often gets hijacked and exploited by marketing that promises: quick fixes, instant relief, and techniques delivered by an “expert” who will do the work for you. The promise feels thrilling because it suggests you don’t necessarily need to change anything about your life — you can keep doing what you’re doing and just get a different result.
But this is an illusion. It’s like expecting weight-loss surgery to transform your health without changing eating or movement habits. Or yearning to “go back to normal” when the truth is that what you thought was “normal” was already shaped by trauma, stress, and oppressive systems that thrive on keeping you in pain.
A Codependent System
The sense of urgency doesn’t occur in a vacuum. The society we live in depends on it.
The system needs you anxious, depressed, and dysregulated to keep itself alive.
You’ve been conditioned to need the system to feel valuable, productive, or worthy. It becomes part of our identity.
It’s a codependent relationship: you feed the system with your labor, obedience, and consumption, and the system rewards you with conditional belonging and the illusion of worth.
The Nervous System and the Urgency Trap
On a physiological level, urgency often comes from being stuck in a sympathetic fight-or-flight state. It’s the body’s attempt to fight against, push away, or flee from something intolerable. That urgent drive can feel like momentum — a promise that if you just work hard enough, you can finally get free.
But this too is a trap. You cannot heal from the same state that was required for survival. Urgency collapses space. It narrows vision. It demands speed over depth.
Healing demands the opposite:
Slowing down.
Creating space instead of collapsing it.
Being with what is, instead of doing to it.
Reenactment in Therapy
Trauma always happens in a hierarchical system: an oppressor and an oppressed, an abuser and a victim, one holding power over the other. These dynamics don’t simply vanish — they show up in therapy too.
Clients may project onto the therapist as the all-knowing expert: “Tell me what to do, fix me, make me better.” They hand over agency because trusting themselves once was unsafe.
Therapists may internalize pressure to perform, to have all the answers, to prove their competence. They risk colluding with the client’s urgency and external locus of control rather than resisting it and working with it.
If this dynamic is unexamined, the therapy space becomes another reenactment of trauma dynamics-such as power dynamics in a hierarchy, coercion, and a sense of urgency — mirroring the very systems (family, religion, education, politics, capitalism) that created the wound in the first place. That is not therapy. That is reenactment. It reinforces the trauma, the survival strategies, and the shame-based identifications that once helped the person survive. This is why it is SO important for therapists to do their own inner work. Without it, therapists run the risk of unconsciously acting out their own wounds on the people who come to them for healing. It becomes the blind leading the blind.
One way a reenactment of survival dynamics can take shape is when a client approaches therapy with an external locus of control — assuming the therapist is the expert who will “fix” them or tell them how to change other people or situations. In this stance, healing is expected to come from the therapist doing something to them, rather than from the collaborative discovery of what arises within them. The therapist is cast as the active agent and the client as the passive recipient, a dynamic that reinforces disconnection from the client’s own capacity to heal and perpetuates the very survival strategies that once kept them safe but now keep them stuck. Another way a reenactment happens is when the client projects an expectation or assumption onto the therapist that they will behave or react in the same patterned way others have engaged with them. They each take on their unconscious roles, continuing to play out the same pattern, always with the same disappointing, painful, but familiar result.
At the same time, therapists themselves may internalize pressure to perform, to have all the answers, or to deliver quick change; to be a “good” therapist. A rewarding object, not even another human with their own feelings and needs. When this happens, they risk colluding with the very systems and strategies that caused them both harm, reenacting the same power imbalance the client has already endured.
An astute therapist will not only notice this pattern when it appears, they expect it, and then they will also notice and separate their own countertransference reactions to it. Their own countertransference reactions can also give the therapist a glimpse into what others may experience in relation to the client, or the patterns that play out between client and those they are in relationship with. This allows them to use this pattern in the therapy session, working directly with the survival strategy, the physiology, and the once split-off primary emotions that arise with it, leading to emotional completion, integrating all the disconnected parts, and restructuring top down, bottom up, and inside out, their entire sense of self.
Meaningful therapy is uncomfortable. It should challenge and stretch you. It gently confronts survival strategies, brings blind spots into awareness, and holds space for shame-based identifications to soften. It shouldn’t just be a continuous validation of every thought and behavior. It’s not about warm fuzzy feelings or just making you feel good. When that is all that happens in the therapy space, growth and healing is no longer on the menu. Meaningful therapy helps the client reclaim agency and integrate the emotions that arise when defenses relax. It refuses urgency and power dynamics, because neither can create the conditions for safety — and without safety, there can be no true healing.
Coercive Control and the Role of Urgency
Coercive control is one of the clearest examples of how urgency is weaponized in relational trauma. It’s not always about physical violence — it’s about domination through surveillance, restriction, manipulation, and fear. The person living under coercive control learns that their safety depends on constant vigilance and immediate compliance.
Urgency is baked into the relationship:
“Answer me right now or you’ll be punished.”
“Do this immediately or else.”
“If you pause, resist, question, deviate from the norm/tradition, or reflect, you’re in danger.”
Over time, the nervous system becomes wired for urgency and external validation and control as a survival strategy. This is one reason why many survivors of coercive control arrive in therapy demanding quick fixes, instant calm, or someone else to take over the responsibility of healing. Why would they think otherwise when that is the way it has always been?
And just as in larger systems — family, religion, education, politics, capitalism — coercive control thrives on power-over dynamics and a sense of urgency to throw you off balance. The oppressor benefits from keeping the victim reactive, small, and disconnected from their own knowing.
Therapy must resist reenacting these dynamics. True healing cannot happen in a reenactment of coercive control, with the therapist positioned as the “expert” who dictates change. Instead, healing requires a safe relationship where agency, time, and curiosity replace pressure, urgency, and domination.
The Seduction of Somatic Therapies
When a potential therapy client first hears about somatic therapy — and is told that the “old way” of therapy was all wrong and this new way will finally fix them, it’s incredibly compelling. Especially when somatic therapy promises that you will not have to go through the telling of your trauma story, simply talking about it over and over again.
But this message is also misleading. If used in this manner, it becomes yet another way to override pain and rush toward a state of “calm,” “relaxed,” or “peaceful”, which gets marketed as “regulation.” Instead of connecting more deeply to themselves, people can end up using these practices or techniques to disconnect even further. It reinforces a familiar survival dynamic: the belief that healing will come from something being done to them by an external expert, rather than through their own inner process. Clients may long to be the passive recipient of change while the therapist or practitioner acts as the active agent. On the surface this feels relieving — a way to finally and quickly bypass pain and rush toward an imagined state of “calm,” “relaxed,” or “peaceful.” Yet in reality, it risks becoming another way of disconnecting from the self, yet another spiritual bypass. Or it just becomes another practice of relaxation or catharsis that never leads to lasting change. The practice or technique becomes a tool to eagerly meet that intense sense of urgency with equal intensity and then cathart it out. This can feel very relaxing and promising, but again, it is not sustainable and in fact can simply reinforce the same pattern of activation and deactivation, never finding integration and sometimes pushing the participant into further fragmentation and regression. At the very least, it becomes no different than your typical yoga class. It has an important function but will not heal a lifetime of complex or developmental trauma. That requires top-down, bottom-up and inside-out relational healing. It requires a titrated (slow), undoing and re-doing over time and in relationship. I’m sorry to tell you, but there is no quick fix to complex or development trauma. But there is hope and there is healing. It just requires creating the conditions to allow for regulation to emerge. And those conditions do not include speed or urgency.
Relaxation was never the purpose of truly therapeutic somatic work. Somatic psychotherapy, at its best, is not about techniques done to you or quick fixes imposed on you. It’s an invitation:
to slow down, (not speed up)
to notice sensations and patterns,
to ask what else is here,
to feel what wanted to happen but never got to,
to discover what arises when we stop rushing and begin to notice.
This is the heart of somatic healing — not rushing to override discomfort, not outsourcing agency to another-- but creating space, reclaiming it by cultivating curiosity, presence, and embodied awareness.
How Larger Systems Exploit Urgency and Pain
This reenactment dynamic is not confined to therapy. It is a mirror of how broader systems of power exploit urgency, pain, and vulnerability to maintain control.
⚖️ Family Systems
Families organized around secrecy, abuse, or dysfunction often rely on urgency, power dynamics, and coercive control: “Don’t make us look bad,” “Get over it,” “Do what I say, now”, and my personal favorite: “stop crying or I’ll give you something to cry about". Power is held by parents or caregivers, while children learn to override their needs.
💒 Religious Systems
Authoritarian or fundamentalist religions thrive on urgency, coercive control, and power dynamics: repent now, obey now, submit now. These systems frame guilt, shame, distrust of the body and emotions as spiritual virtues, while reinforcing the hierarchy of leader → follower.
📚 Educational Systems
Schools reward obedience, speed, and compliance over depth or critical thought. Children learn to override their bodies: hold it until the bell, sit still, produce results fast. Urgency and disconnection becomes a lifelong survival pattern.
⚖️ Judicial and Carceral Systems
Courts and prisons thrive on punishment and compliance. Trauma responses like freeze or dissociation are punished as defiance or seen as weakness, an intentional choice, or moral failing. “Do this now or face consequences” becomes institutionalized.
🏛️ Policy and Bureaucratic Systems
Public policy prizes efficiency over humanity. Test scores, quick outcomes, job placements — all reinforce urgency and reduce people to numbers.
👑 Authoritarian and Fascist Systems
Urgency, coercive control, and power dynamics suppresses dissent: “Obey now, don’t question.” Trauma survivors who’ve internalized urgency are more vulnerable to authoritarian control.
💸 Capitalist Systems
Capitalism thrives on urgency and disconnection. “Buy this now, don’t think about it or it will be gone! You need it now so you can feel better!” Productivity and speed are glorified, rest is shamed, and overextension is rewarded. Trauma survivors conditioned to equate worth with doing more and buying more become ideal workers and consumers.
👨👩👦 Patriarchal Systems
Patriarchy exploits urgency through gendered roles: women must multitask, men must perform, no one should show vulnerability. Slowing down, re-connecting, and questioning the status quo could destabilize the hierarchy.
⚕️ Medical-Industrial Complex
The healthcare system profits from quick fixes — pills, surgeries, brief interventions. The focus becomes on treating the symptoms of the sick instead of prevention and wellness. Long-term relational healing is undervalued because it cannot be commodified as easily. It costs too much and again, takes too much time and insurance companies don’t want to pay for it.
📰 Media and Social Media
Media ecosystems thrive on urgency: breaking news, outrage, comparison, algorithms, marketing through instant gratification without even leaving the house. Likes, dislikes, comments. Calm, regulated humans are less profitable than anxious, hypervigilant ones.
🌎 White Supremacy and Colonial Systems
Colonialism and white supremacy weaponize urgency by keeping entire populations in survival mode through resource deprivation, disconnection, and fear. A dysregulated population cannot resist or organize effectively.
The Through-Line: Who Benefits From Your Pain?
The thread that connects all these systems is simple: they benefit when you are in a state of protection over connection; pain, urgency, disconnection, distrust of self and others.
When you stay dysregulated:
You work harder for less.
You obey authority without question.
You consume more to soothe yourself.
You distrust your own agency and defer to external control.
You don’t listen to your body, emotions, intuition or gut instincts.
This is why healing cannot happen in a survival state marked by urgency. Slowing down, reclaiming agency, and refusing to collude with urgency is not just therapeutic — it is profoundly political by resisting and refusing to continue the same patterns keeping you stuck.
What Healing Really Requires
Healing is not an act of willpower. You cannot force it, push it, or schedule it. Healing is not urgent.
Instead, healing is:
A devotion to oneself. Choosing presence, curiosity, and care over collapse and speed.
A process of remembering. Reconnecting with parts of yourself that had to go into hiding.
Creative and curious. Approaching the body and psyche with openness, not a script or someone else’s interpretation.
Slow and unfurling. Like a flower opening toward light, healing stretches little by little, savoring each expansion.
Healing does not arise from urgency. It arises from safety — and safety requires space, time, and relationship.
Conclusion
Urgency, hierarchies, power dynamics, coercive control, and the seduction of quick one-size-fits-all somatic fixes are all part of the same cycle of trauma dynamics. They repeat the survival strategies and power imbalances that once kept people alive but now keep them stuck. When clients approach therapy expecting the therapist to be the active agent who “does the work” to them, or when therapists internalize pressure to perform and deliver quick change, both risk reenacting the very dynamics that created the wound.
The same is true of systems that promise healing through urgency, shortcuts, or authority — whether in families, religions, schools, politics, or consumer culture. Each thrives on urgency and externalized control. Each benefits from keeping people reactive, dependent, and disconnected from their own agency. They want you to continue to “need” whatever object, service, or belief they are “selling”.
Real healing refuses to collude with these dynamics. It does not replicate urgency, hierarchy, or externalized control. Instead, it creates safety — the one condition that trauma never allowed. Safety makes room for slowing down, for noticing, for curiosity. It helps clients reclaim agency, feel what was once impossible to feel, and discover the aliveness that emerges not through being “fixed,” but through being present. Being present WITH the pain, the joy, the grief, not bypassing or “regulating” (really it is managing it, not regulating it) it away once again, turning against yourself and exiling yourself back to the shadows. It becomes a missed opportunity.
To heal, we must step out of the state we survived in. That is the paradox, and the path: survival demanded urgency and control, but healing unfolds only through space, safety, and relationship.
The therapist’s role is not to collude with urgency, but to resist it — to help clients slow down, reclaim their agency, and learn that they no longer need to reenact survival patterns if you are no longer in danger. In doing so, therapy becomes more than symptom management. It becomes an act of resistance against the systems that profit from pain, and an act of devotion to the aliveness that unfolds only when we slow down and make space for it, and give it all the time it needs.
Written by Fay O’Neill, LCSW
Embodied. Therapy and Healing Arts — Committed to trauma-informed care, systemic awareness, and consumer protection.

The Healing Power of Music

James Hetfield of Metallica surrounded by screaming fans at a concert.
Let’s talk about music as therapy. Music as medicine. Music as meditation. Music as healing. The genre of music that I have in mind while writing this is rock and metal, although I know other genres would apply as well. But hear me out, when it comes to metal music. In my studies of trauma treatment there are many key ingredients that lead to healing: choice making, empowerment, non-coercion, shared authentic experience, interoception, safety, and attunement. I would argue that metal music delivers on all of these. In Flea’s induction speech of Metallica into the Rock & Roll Hall of Fame, he asserts “when I hear Metallica, I get this feeling that they are doing something that they HAVE to do, like there is this thing in them wound up so tight that they have to let it out, let that thing uncoil, it has to be released, an infinite well of sadness, a hell of a lot of pain and anger, but mostly a lot of love for the process that they have created for releasing this stuff. It is always really absurd to me when I hear people speak of heavy music, angry, aggressive music, as being negative or (un)healthy for children and so on, bla bla bla. Firstly, the playing of ferocious music is the healthiest release of anger for the performer of it. It is alchemy, it is a metamorphosis, it is turning something potentially destructive and a source of misery into something beautiful, something rocking and something uplifting for the band and for the audience. The tradition of pain and hurt being a muse for great art is one of the greatest rites of passage for any artist, and that which touches us most deeply. Anyone who has ever been to a Metallica show and banged their head and thrown up the devil horns has been a part of something great for humanity. All those kids at a show rocking so hard to the brutal beat of Metallica have come together for those couple of hours in a way as healthy as any spiritual exercise, any group meditation, any love-in, anything. It is uplifting and it brings people together. I love all music, but I say Metallica has done as much to bring people together and bring joy into their lives as any “hippie, peace and love music” ever has. For the people who give it up and get rocked by Metallica, the world is a lot less of a lonely place. When a person gets rocked into their music, everything else disappears and that person is just one with the rock. It is an inexplicable awesome thing and I bow down to it”. I couldn’t have said it better, Flea.
Let’s consider the lyrics to Metallica’s One.
I can't remember anything
Can't tell if this is true or dream
Deep down inside I feel to scream
This terrible silence stops me
Now that the war is through with me
I'm waking up, I cannot see
That there's not much left of me
Nothing is real but pain now
Hold my breath as I wish for death
Oh, please, God, wake me
Back in the womb, it's much too real
In pumps life that I must feel
But can't look forward to reveal
Look to the time when I'll live
Fed through the tube that sticks in me
Just like a wartime novelty
Tied to machines that make me be
Cut this life off from me
Hold my breath as I wish for death
Oh, please, God, wake me
Now the world is gone, I'm just one
Oh, God, help me
Hold my breath as I wish for death
Oh, please, God, help me
Darkness
Imprisoning me
All that I see
Absolute horror
I cannot live
I cannot die
Trapped in myself
Body my holding cell
Landmine
Has taken my sight
Taken my speech
Taken my hearing
Taken my arms
Taken my legs
Taken my soul
Left me with life in hell
I used to think this song was about being in actual war, like Vietnam and the world wars. And the beauty of it is that it can be. But after watching an interview of James Hetfield by Howard Stern, James recounts how this song was inspired by a book called Johnny Got His Gun, who was a “prisoner in his own body” after being wounded during war, and that he “related to that, because I felt that…being stuck in your own skin and how uncomfortable that can feel and that would be like the ultimate hell, where you can’t communicate to anybody”. James attributes his ability to relate to this to his traumatic upbringing. He was raised in a Christian Science household and not allowed to receive any medical treatment or education on health. His father abandoned the family when he was 13 and his mom died of cancer a few years later, leaving him orphaned, angry, and feeling alone. You can literally feel his pain and suffering in this musical testimony. For others who have been through their own pain and suffering, songs such as these are like salves to their wounds. It speaks to trauma, no matter how it is inflicted.
Metal bands, such as Metallica, speak to the pain of a generation, that continues to translate and reverberate as each new generation comes of age. It is a shared humanity. A shared pain that finds connection, release and transformation through its lyrics, it’s screaming rage and passion, its head banging and thrashing. It invites its fellow survivors of misery to take a stand, take back their power, use their voice, and give a big middle finger to those who have perpetrated against them, caused them pain, or told them that they were not good enough. When I listen to this music, it is a full body and soul experience, calling me to move my body in such a way that is a welcome release for pent up tension, energy, and emotion. It is truly visceral. You can’t help but be in an intimate relationship with your body as it absorbs the potent and commanding musicality on a cellular level. It taps into one’s deepest recesses, the dark places, and has the power to move someone from the prison of disconnection, emptiness, and shame, to a state of mobilization, vitality, and empowerment, by creating a container and context to safely express these most intimate parts of ourselves. Whether you are at home by yourself with the stereo turned to the max, or surrounded by thousands of other screaming fans, there is a strong sense of belonging to something greater than yourself. It is every bit a spiritual experience. That powerful and potent sound brings voice to your innermost demons and injects you with an overwhelming feeling of finally being seen, heard, validated, and vindicated, as you use your own powerful voice to scream the words that speak your pain. Power and choice is back in your control, and you are welcomed with open arms that do not care where you came from, what mistakes you made in the past, who you voted for, who you love, or how much money you have in the bank. Before you even realize what has happened, you have found safety and connection in a relationship and you once again, or finally, know who YOU are, because that certainty, embodiment, and profound felt-sense of your true self is reflected back to you with complete acceptance, vulnerability, and intimacy in those seemingly angry and aggressive lyrics, the powerful and intricate guitar harmonies and solos, and those thunderous and all-consuming drums. As the song comes to a brutal end, your turmoil spent, you are renewed, replenished, transformed, and ready to take on the world. Those who condemn and demonize this type of music, in my opinion, are simply scared. You cannot sit with others’ pain, if you cannot sit with your own, and metal music is transparent and in your face about the most painful of human emotions. To be able to be that raw and truthful in expressing yourself and sharing your pain with the world is an act of bravery, vulnerability, and love, which demands our respect and gratitude. Their strength opens the door for the rest of us to do the same and in doing so, we no longer feel disconnected and alone. It says “I see you, I feel you, and I feel it too, and we are in this together”. This, my friends, is the antidote to trauma.
What bands or musicians have inspired you or aided in your own healing? Feel free to share how, if you’re brave enough